

Many people can play pickleball with arthritis, especially osteoarthritis, if symptoms are well managed. The key is controlling total court time, warming up properly, building strength, and watching how the joint feels later that day and the next morning. Pain that worsens, causes limping, or comes with swelling deserves more caution.
If you’re an older pickleball player with arthritis, you’ve probably had this experience:
Your knee feels stiff getting out of the car.
You walk onto the court wondering whether you should even play.
Ten minutes later, you’ve warmed up, the joint feels better, and suddenly you’re chasing dinks like nothing happened. Then that evening—or the next morning—it talks back.
That pattern is exactly why arthritis and pickleball can be confusing.
The bigger issue isn’t whether pickleball is simply “good” or “bad” for arthritis. For most older players, it comes down to how much play the joint can handle without triggering a meaningful flare later that day or the next morning.
That’s the useful way to think about it.
Because for many people with arthritis, movement is not the enemy. Exercise is actually a core part of treatment, especially for osteoarthritis. But pickleball is also not a gentle walk around the block. It asks you to crouch, stop, lunge, shuffle laterally and occasionally make one very optimistic sprint for a ball you probably should have let go.
So yes, many people with arthritis can play pickleball. The trick is learning the difference between productive loading and a flare you keep feeding.
First: “Arthritis” Is Not One Thing
When older recreational players say they have arthritis, they’re often talking about osteoarthritis, the wear-and-change process commonly affecting knees, hips, hands and other joints.
Osteoarthritis behaves differently from inflammatory conditions such as rheumatoid arthritis.
With osteoarthritis, regular exercise is strongly recommended because it can improve pain, function, strength and quality of life. Major clinical guidelines treat exercise as a central part of management rather than something people should avoid.
Rheumatoid arthritis is different because the immune system drives inflammation. People are still encouraged to remain active, but during a true flare—especially with swollen, hot and markedly painful joints—activity may need to be reduced and balanced with more rest.
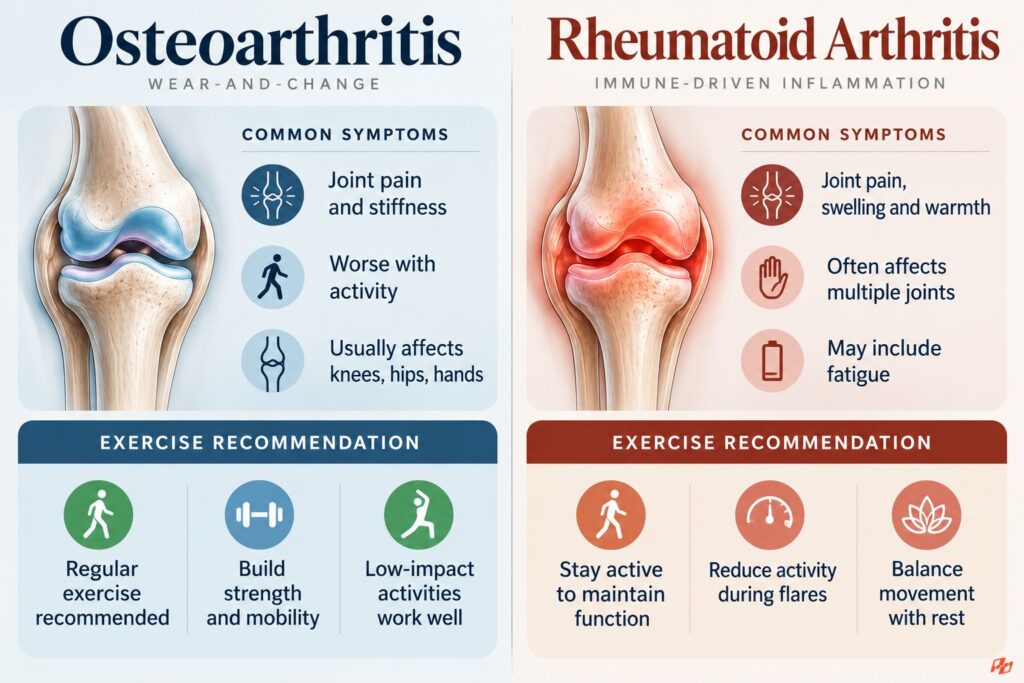
That distinction is important enough that anyone with significant arthritis should know what type they actually have, not just that “the doctor said arthritis.”
Can Pickleball Actually Make Arthritis Flare?
It can increase symptoms. That does not automatically mean you are damaging the joint every time it hurts.
One of the hardest things about arthritis is that symptoms and damage are not perfectly interchangeable.
People starting or increasing exercise can experience temporary increases in pain, stiffness or swelling. The CDC specifically notes that some discomfort can occur when beginning a new activity, and that symptoms often improve as the body adapts.
Pickleball makes that particularly interesting because you may feel fine while playing.
Movement warms the tissues.
Stiffness decreases.
Your attention shifts away from the joint.
Then you cool down and realize: “Oh. My knee definitely noticed those three games.”
That delayed response is useful information.
Instead of judging a session only by how the joint feels at 10:30 a.m. while you’re winning 9–7, pay attention to: how it feels later that day and the following morning.
That gives you a better picture of whether the dose was appropriate.
Think of Your Arthritis Like a Volume Knob, Not an On/Off Switch
A lot of people make arthritis binary.
Feeling good = play normally.
Feeling bad = don’t play.
But there are many variables you can change before going all the way from three hours of open play to sitting on the couch.
You can change:
- duration
- number of games
- intensity
- court coverage
- recovery between games
- frequency per week
That matters because the body responds to total load, not merely whether you stepped onto a pickleball court.
Suppose your knee tolerates: four games reasonably well.
Game five makes it ache.
Game six makes you limp afterward.
The better question isn’t whether pickleball is “bad” for your knee. It’s whether your current amount of play is more than your knee can handle comfortably.
If five games feel fine but six leave you limping, that gives you something useful to work with: adjust the load before blaming the sport.
The CDC similarly recommends reducing the frequency, duration or intensity of activity when arthritis pain increases rather than automatically abandoning physical activity altogether.
The Most Important Question Comes the Next Morning
Here’s a simple experiment. After you play, mentally rate the troublesome joint:
- before play
- a few hours after
- the next morning
You don’t need an app. Just notice the pattern.
If you play for 90 minutes and your knee is mildly tired afterward but essentially back to its normal baseline the next day, that’s very different from playing 90 minutes and waking up the next morning with much more pain, swelling and reduced movement.
There is no universally accepted pain number that tells every person with arthritis when they should or shouldn’t exercise; clinical guidelines explicitly acknowledge that exercise has to be individualized.
So instead of chasing a magical pain score, look for your repeatable response. That becomes your personal workload data.
Pickleball Has a Strange Mix of “Joint-Friendly” and “Not-So-Friendly”
Pickleball sometimes gets described as low impact. That needs some nuance.
Compared with tennis, there’s generally less court to cover, and a sports-medicine specialist at Hospital for Special Surgery describes pickleball as less physically demanding than tennis or racquetball.
But pickleball still includes things arthritic joints may dislike:
- quick lateral pushes
- sudden stops
- repeated knee flexion
- lunges
- backpedaling
- unplanned changes of direction
And this is especially relevant for older players.
Older adults make up a substantial share of pickleball-related injuries, and falls are one of the most common injury mechanisms reported in emergency-department studies.
That doesn’t mean pickleball is inherently unsafe for older adults. It means that when we’re talking about arthritis and longevity, balance and movement quality matter just as much as the sore joint itself.
Warm Up Until You Feel Like a Pickleball Player, Not a Passenger
For someone with arthritis, walking onto the court cold and immediately starting competitive points is a terrible test of how the joint really functions.
Arthritis specialists commonly recommend at least several minutes of gradual movement before harder exercise. Dynamic movement is generally preferred before activity rather than long static stretching of cold tissue.
For pickleball, I’d keep it very practical.
Spend five to ten minutes getting progressively more athletic.
Walk.
Then shuffle gently.
Move the ankles and hips.
Perform a few shallow squats or sit-to-stands if comfortable.
Take small lateral steps.
Then dink.
Then hit controlled volleys and groundstrokes.
Only after that start asking your body for sudden stops and reaches.
A physical therapist interviewed specifically about pickleball warm-ups makes the same distinction: the goal isn’t simply stretching tissue; it’s preparing the nervous and musculoskeletal systems for the actual movements the sport requires.
For an arthritic knee or hip, those first ten minutes can tell you a lot.
If movement makes the joint progressively freer, that’s useful. If the joint becomes progressively sharper, more swollen or less stable, that’s useful too.
Strength Training May Help Your Pickleball More Than Another Hour of Pickleball
This is where many older recreational players get the order wrong. They want to keep playing pickleball, so they play more pickleball. But the muscles around the joint are part of its support system.
Strengthening is consistently recommended for osteoarthritis because stronger muscles can improve function and help support the affected joints.
For a knee, that may involve the quadriceps, hamstrings, calves, and hip muscles.
For the hips, the glutes and surrounding muscles become especially important.
For hand arthritis, grip and hand function may need their own approach.
You don’t need to turn yourself into a powerlifter.
But two sensible strength sessions each week may do more for your ability to keep playing than simply adding two more open-play sessions.
For older players with arthritis, that might mean simple, controlled work such as sit-to-stands or box squats, step-ups, calf raises, glute bridges, supported split squats, light hamstring work, banded side steps, and basic single-leg balance. The goal isn’t to train like a competitive lifter—it’s to keep the muscles around the hips, knees, and ankles strong enough to absorb force and control movement.

The CDC recommends muscle-strengthening work at least two days per week, alongside aerobic and balance activity.
What About Playing Through Pain?
This is where players need a little judgment.
A stiff knee that loosens as you move is one thing.
A sharp pain that changes the way you walk is another.
The CDC recommends getting medical advice for pain that is sharp, stabbing and constant; causes limping; persists significantly after activity; worsens at night; or comes with swelling that doesn’t settle. A joint that becomes markedly hot, red or swollen also deserves attention.
That gives us a much more useful way to interpret pain.
🟢 Mild familiar stiffness: often manageable.
🟠 Mild soreness after an unusual workload: worth monitoring.
🔴 Pain altering your mechanics: much more concerning.
Sudden sharp pain, major swelling, heat, redness or inability to bear weight normally: stop treating it as ordinary arthritis.
And if you have inflammatory arthritis, a true flare deserves a different conversation than the normal post-pickleball aches of osteoarthritis.
Don’t Let Pain Medication Become Your Playing Strategy
Pain medication can absolutely be part of arthritis treatment, and options such as topical or oral NSAIDs are commonly used for some forms of osteoarthritis.
The important point is why you’re taking it.
If you’re using medication as part of your normal treatment plan, that’s one thing.
If you’re taking it mainly so you can push through worsening pain and squeeze in another hour or two of pickleball, that’s different. You may be masking a signal that your joint has already had enough for the day.
So instead of asking, “What can I take so I can keep playing?” it may be more useful to ask whether you should shorten the session, take longer breaks, or play fewer games.
Medication can help manage symptoms. It shouldn’t become the thing that lets you repeatedly ignore them.
Your Best Pickleball Week May Have Less Pickleball In It
This is the part nobody wants to hear. Suppose you currently play:
Monday
Tuesday
Wednesday
Friday
Saturday
And every Thursday morning your knee is furious. You may not have a knee problem that requires quitting pickleball. You may have a schedule problem.
Two harder days separated by recovery may work better than three consecutive sessions.
Or perhaps open play for 60 minutes works beautifully while 2½ hours doesn’t.
Or doubles is comfortable while singles isn’t.
Or a lower-intensity drilling day between harder match days keeps you moving without stacking as much joint stress.
This is where managing arthritis becomes almost like managing training. You’re searching for the amount of stress that creates adaptation without repeatedly overwhelming recovery.
And that amount can change.
A joint may tolerate more after months of consistent strength work. It may tolerate less after illness, travel, poor sleep or a flare.
You don’t need the same weekly prescription forever.
So, Is Pickleball Safe With Arthritis?
For many people, yes—with some important qualifiers.
Osteoarthritis itself is not generally a reason to avoid physical activity. Exercise is strongly recommended as part of treatment, and most people with OA can benefit from some form of regular movement.
But pickleball places more unpredictable load on the body than classic low-impact exercises such as cycling or swimming.
So your job is not to prove that you can tolerate unlimited pickleball. It’s to figure out the version your body handles well.
Maybe that’s four games instead of eight.
Maybe you need a longer warm-up.
Maybe strength training twice a week dramatically changes what your knee tolerates.
Maybe singles is no longer worth it.
Maybe you’re perfectly capable of playing hard—but not on three consecutive days.
And if pain is sharp, worsening, causing a limp, producing marked swelling or heat, or behaving very differently from your normal arthritis, that’s the point where self-experimentation should stop and a clinician or physical therapist should take a look.
The goal isn’t to make an arthritic joint completely silent before you’re allowed to play. For many older players, that’s unrealistic.
A much better goal is this:
Play enough pickleball to help your body stay strong and active—without repeatedly making the next day worse.
That’s the balance worth finding.




